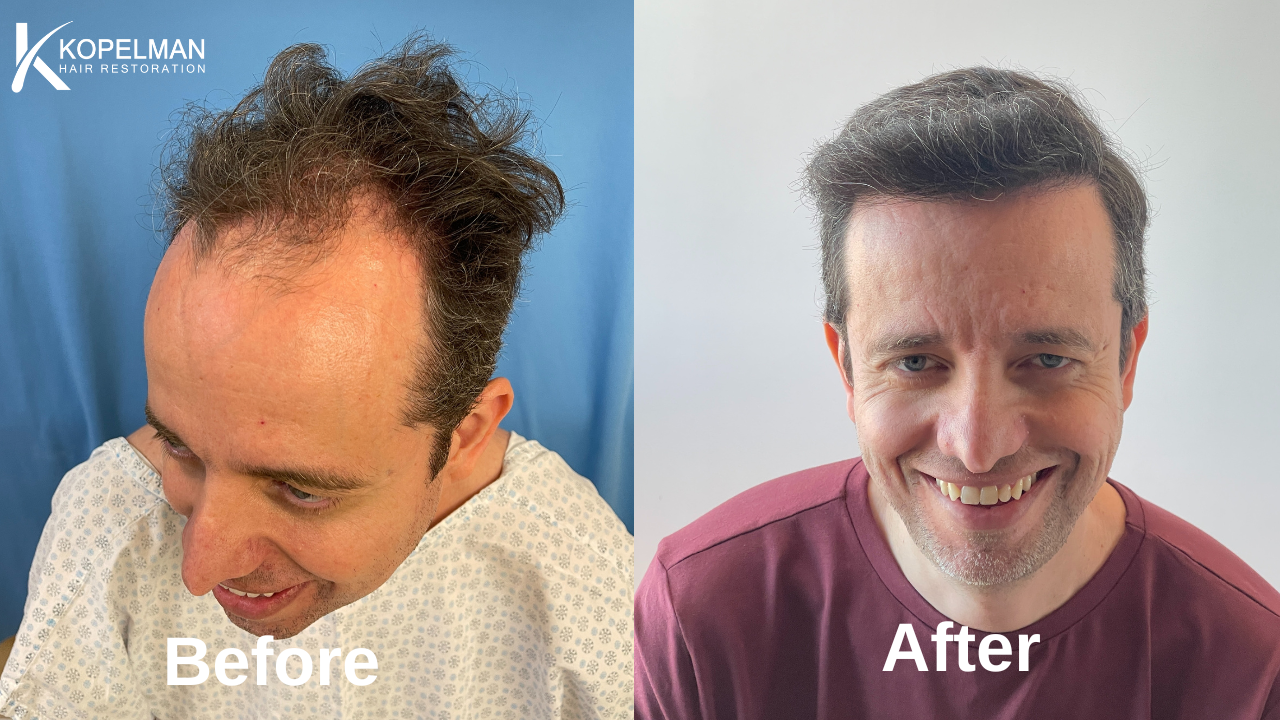
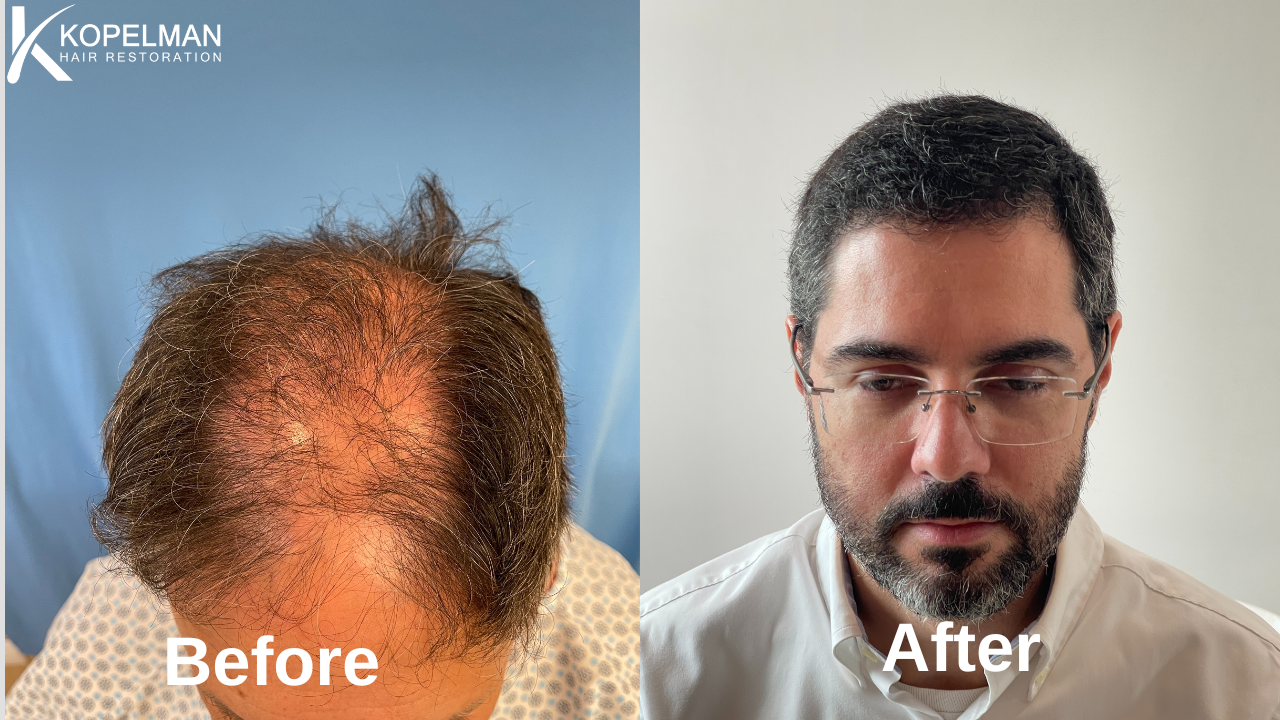
At Kopelman Hair, the frontal edge is mapped through a personalized process tailored to facial structure and long-term goals. Dr. Kopelman earned his medical degree at New York Medical College and practices in New York City and Palm Beach County.
He focuses on natural, age-appropriate results that blend seamlessly with existing growth.
The Anatomy of a Natural Hairline
A believable result is not one flat line; it is an extended zone roughly 2 to 3 cm deep that bridges the bare forehead to the denser scalp behind it.
Surgeons typically plan it in three connected zones, a structure documented in the clinical literature on frontal restoration (Shapiro & Shapiro, peer-reviewed).
The transition zone is the most forward strip, kept soft, irregular, and slightly see-through. The defined zone sits just behind it and carries more density and definition.
The frontal tuft, a small oval at the center, holds the highest concentration of grafts and drives the impression of fullness.
| Zone | Role | Graft type used | Relative density |
|---|---|---|---|
| Transition zone (front 0.5 to 1.0 cm) | Soft, irregular, slightly see-through leading edge | Single-strand grafts | Lowest |
| Defined zone | Adds substance and definition behind the front | Mostly two-strand grafts | Medium to high |
| Frontal tuft | Central oval that drives the impression of fullness | Higher share of three-strand grafts | Highest |
Hair Transplant Edges at the Temples
Hair transplant edges at the sides matter just as much as the front. The frontal-temporal angle is the corner where the front line meets the temple; flattening or overfilling it is a common error that reads as artificial.
The temporal points, the small triangular protrusions near the temples, frame the face and prevent the forehead from looking wider than it should.
Where the Front Line Should Sit
Many guides start with the “four-finger rule,” the idea that the leading edge should sit about four fingers above the brows. It is a rough starting point at best, because finger width varies from person to person, so surgeons treat it as a sanity check rather than a measurement.

A more reliable approach places the central starting point roughly 7 to 10 cm (about 3 to 4 inches) above the brow ridge, in line with the older 8 to 10 cm rule of thumb cited by surgeons, then adjusts within the gentle curve where the forehead meets the scalp. From there, the line is tailored to bone structure, the extent of loss, and donor supply.
Whether someone has a normal or larger forehead, the goal is harmony, not a fixed number.
What Is a Normal Forehead Size in Fingers?
A normal forehead size in fingers is about four, measured with the fingers held flat and together from the brow line to the hairline. That works out to roughly 7 to 8 cm, or about 3 inches, for most adults.
| Fingers above the brow | Approx. height | What it usually means for planning |
|---|---|---|
| 3 fingers | About 5 to 6 cm (about 2 in) | Compact forehead; little room to lower the edge, so planning focuses on shape and the temples. |
| 4 fingers | About 7 to 8 cm (about 3 in) | Typical adult proportion and the usual reference for a natural central starting point. |
| 5 fingers | About 9 to 10 cm (3.5 to 4 in) | Taller forehead; a slightly lower edge or a curved design can add balance. |
| More than 5 fingers | Over 10 cm (over 4 in) | Very tall forehead; may suit a lower edge or hairline lowering surgery, depending on donor supply. |
Is a 5 Finger Hairline Good?
It depends on the face. At about 9 to 10 cm, a five-finger forehead reads as taller than average; some patients are comfortable with it, while others prefer a slightly lower line to balance their proportions. A 4 inch forehead (about 10 cm) sits at the top of the usual range.
For some patients, restoring a more youthful frame means lowering the edge just enough to balance a tall forehead, often described as more than four fingers in height.
A higher central point may be the right call when loss is advanced or donor supply is limited.
For a very tall forehead, hairline lowering surgery is a separate surgical option that moves the scalp forward.
When planning a frontal restoration, Dr. Kopelman assesses not just recession but the ideal starting point based on facial thirds and forehead height.
Key Factors in Planning
Several variables influence the optimal position of the front line, including facial features, age, ethnicity, and the type of loss involved. No single template fits everyone, so there is no one best hairline design for hair transplant; the best plan is drawn for each face individually.
Customizing the Front Line to Facial Structure
Your features help decide the ideal shape. A round face often suits a softer, curved edge, while a square face may carry a straighter line well. Men and women need different approaches, since male pattern loss tends to recede more at the temples.
Facial balance often goes beyond the scalp. Many people exploring restoration also look into eyebrow hair restoration in NYC to maintain facial proportions.
Hairline Design for Women
Female hairlines are generally rounder, lower, and more closed than male ones, with far less temple recession. The 5A5P principle, published in Plastic and Reconstructive Surgery Global Open, breaks female design into five areas (frontal area, frontotemporal recess, temporal peak, infratemple area, and sideburns) and five key points.
Instead of borrowing a male template, the plan follows these landmarks so the line frames the face softly. Women with thinning at the temples are first checked for causes such as traction or frontal fibrosing alopecia, since a transplant works best once the loss is stable.
Pricing for women’s cases is covered in the female hair transplant cost guide. You can also learn more about correcting high or uneven hairlines, especially for women experiencing frontal recession.
Age and Long-Term Positioning
A strong plan accounts for aging. A line set too low may not wear well over decades, while one placed too high can look severe.
The right balance keeps the result believable for the long term.
Donor supply is also finite, so every graft spent on a very low line is one not available for future loss. Patients with androgenetic alopecia or frontal fibrosing alopecia should also plan for future shedding.
Ethnicity and Natural Variation
Different ethnic backgrounds carry different patterns. Texture and the way loss progresses vary. Patterns vary within every group, but some patients, including some Black, Middle Eastern, Asian, and Hispanic patients, have broader, flatter fronts with less temple recession, and the plan adjusts to the individual.
Strand thickness, curl, and contrast with the scalp also change how visible each graft looks.
People with traction alopecia, common with tight hairstyles, may need extra care.
Shape: Straight vs. Curved
The right contour depends on facial shape, genetics, and preference. Some people prefer a structured, straighter look, while others like a softer, rounded edge. A curved design is often chosen for those with a tall forehead, since it visually reduces height and adds balance.
Density and Gradual Transitions
A natural front should shift density smoothly, copying how real growth thins toward the edge.
Surgeons build density in steps, lowest at the very edge and rising toward the central tuft, with exact figures set by donor supply and the patient’s goals. Adding density in the defined zone also makes the front look fuller without crowding the leading edge, so there is no sudden wall of grafts.
Direction and Angle
Placed follicles should match the natural exit angle to avoid an artificial look. The angle changes by region: steeper in the mid-scalp, more acute along the front, and nearly flat at the temples.
| Do | Avoid |
|---|---|
| Plan for future thinning, especially in younger patients | Setting the leading edge too low |
| Use single-strand grafts at the very front | Packing multi-strand grafts into the front row |
| Keep micro and macro irregularity along the edge | Flattening or overfilling the frontal-temporal angle |
| Match the natural exit angle by region | Misdirecting grafts or angling them upward |
| Stay conservative when donor supply is limited | Relying on finger-counting alone for placement |

Common Mistakes to Avoid
The biggest error is setting the leading edge too low, which looks unnatural and worsens with age. Relying only on counting fingers on the forehead, without adjusting for proportion, can push placement too high or too low. Another frequent mistake is ignoring future loss, which can later leave isolated growth surrounded by thinning scalp.Non-Surgical Options for Enhancement
Some treatments slow the loss or improve the look of the front without an operation.- Medications:
- Finasteride (Propecia): Blocks DHT, slowing thinning in androgenetic alopecia.
- Minoxidil: A topical solution that stimulates growth.
- Supplements: Vitamins and minerals that support follicle health.
Recovery and Aftercare
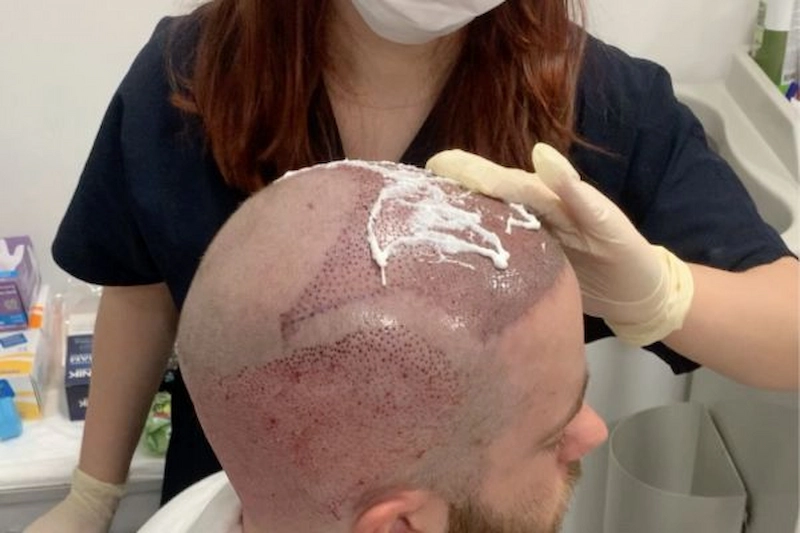
Immediate aftercare tips:- Avoid touching or scratching the treated area.
- Sleep with the head elevated to reduce swelling.
- Use prescribed medications and shampoos as directed.
- First 2 weeks: Scabbing and healing, with shedding of the transplanted strands starting soon after.
- 3 to 4 months: Early signs of new growth.
- 6 to 12 months: Noticeable improvement in density.
- 12 to 18 months: Strands mature and thicken for the final result.
Hairline Design Examples
When you review before-and-after cases, study the front edge up close and from the side. A natural result usually shows:- A soft, uneven leading edge with no visible rows of grafts.
- Temples that taper gently into the sides, with a defined frontal-temporal angle.
- Density that builds gradually from the edge toward the center.
- For women, a rounder, lower line that frames the face without a sharp corner.
How to Choose the Right Clinic
While a basic visual app might offer a rough estimate, only a qualified surgeon can build a customized, natural-looking plan. What to look for in a surgeon:- Board certification and experience in frontal design.
- A strong portfolio of before-and-after results
- A surgeon who personally draws the front line and can explain why it sits where it does.
- What is my expected growth timeline?
- How will my front line be designed for my features?
- What techniques do you use to plan for future loss?
- Who draws the front line, and who places the grafts?
What to Expect on Cost
Frontal-focused work usually requires fewer grafts than full coverage, typically 500 to 2,000 grafts, depending on the extent of recession and the density goal. The ranges below reflect current estimates at Kopelman Hair.| Scope of work | Typical graft range | Estimated cost | What it usually covers |
|---|---|---|---|
| Frontal-focused restoration | About 500 to 2,000 grafts | $25,000 to $40,000 | Rebuilding the leading edge and front zone for a fuller frame |
| Front plus partial mid-scalp | About 3,000 grafts | $25,000 to $35,000 | Front coverage extended into thinning behind it |
| Extended coverage | About 5,000 grafts | $30,000 to $40,000 | Front, mid-scalp, and crown planned together |
| No-shave FUE | Varies | $30,000 to $40,000 | Transplant without shaving the donor area |
| Female hairline transplant | Varies | $25,000 to $40,000 | Rounded, lower female design |
| Hairline lowering surgery | Not graft-based | $25,000 to $40,000 | Moves the scalp forward to shorten a tall forehead |
| PRP support | Not applicable | $1,500 per session | Supports early-stage thinning around the front line |
For a full breakdown, see the guide on hairline transplant cost and what drives pricing, or the hair loss clinic prices page.
Factors that influence price:
- The extent of loss and the number of grafts needed.
- The type of loss, such as androgenic alopecia or frontal fibrosing alopecia.
- The clinic’s reputation and location.
- Maintenance care, such as finasteride (Propecia), to maintain results.
- A consultation is $350. It covers a full year of care, with as many visits as needed, in person or virtual, and it does not go toward surgery.
Surgery vs. Temporary Solutions
Medications like finasteride (Propecia) slow the loss, but a transplant offers a lasting result. Medication is ongoing, while a transplant is a single procedure, so the right mix depends on the extent of loss and donor supply. Patients with a history of pattern loss may combine both for the best outcome.
Hairline Design for Hair Transplant FAQs
-
1. How much does a hairline transplant cost?
At Kopelman Hair, an FUE transplant typically runs $25,000 to $40,000, with graft count, extent of loss, and design complexity setting the final quote. The cost section above breaks down the main ranges.
-
2. How many grafts are needed for a hairline transplant?
Frontal-focused work typically takes 500 to 2,000 grafts. Wider recession or a higher density goal moves the plan toward the 3,000 to 5,000 graft ranges in the cost table.
-
3. How long does it take for a transplanted hairline to grow in?
Scabs clear within about 2 weeks, the transplanted strands shed over the following weeks, early growth appears at 3 to 4 months, and noticeable density builds by 6 to 12 months. Full maturation can take up to 18 months.
-
4. Can a bad hairline from a previous transplant be fixed?
Often, yes. A line that sits too low or looks too straight can be softened with added grafts or by repositioning existing ones. The best approach depends on the original technique and the donor supply that remains.
-
5. Do I need medication after a hairline transplant?
Transplanted follicles keep growing, but the native strands around them can still thin. Medical management such as finasteride or minoxidil helps protect the surrounding growth and the overall look of the new front line.
Your Restoration Journey
Whether you are addressing androgenic alopecia, frontal fibrosing alopecia, or a receding hairline, expert care matters, especially for women seeking natural, long-term results.
Dr. Kopelman and his team provide customized plans built around each patient. Schedule a consultation today.